Rule status: Proposed, not in effect. Last reviewed in fall 2026. See docket. Educational information, not legal advice. Prestige Veteran Medical Consulting is not a law firm or VA-accredited claims agent.
We monitor the Federal Register docket for updates.
Sleep apnea is one of the most commonly claimed disabilities among veterans. CPAP manufacturers have estimated that at least 8 million people sleep with a CPAP machine each night. The Department of Veterans Affairs (VA) has proposed changes to the way it rates this condition, but the proposal is not final or in effect. Many veterans rely on their VA disability ratings for financial support, and any final changes may affect future claims.
Below, we summarize the current rating system and proposed VA sleep apnea rating changes, including public commentary by accredited VA attorney Rebecca Deming of ProVet Legal.

Table of Contents
What is Sleep Apnea in Veterans?
Sleep apnea is a serious sleep disorder in which breathing repeatedly stops and starts during sleep. It is a prevalent condition among veterans, often linked to PTSD, traumatic brain injuries, facial or neck injuries, and prolonged exposure to smoke, burn pits, dust, and chemical agents during service. These risk factors can damage the respiratory system and disrupt the brain’s ability to regulate breathing.
There are three main types, namely,
- Obstructive Sleep Apnea (OSA)
- Central Sleep Apnea (CSA)
- Complex Sleep Apnea
Common sleep apnea symptoms include loud snoring, choking or gasping for air, excessive daytime sleepiness, and difficulty concentrating. If untreated, sleep apnea can lead to complications like high blood pressure, heart disease, diabetes, atrial fibrillation, and even death due to low blood oxygen.
A study published in the American Journal of Health Promotion found that obstructive sleep apnea (OSA) was diagnosed in 21% of veterans, more than double the 9% prevalence observed in nonveterans.
Veterans diagnosed with sleep apnea may also be eligible for VA disability benefits if the condition is connected to their military service.
Key Requirements for Service Connection
To qualify for VA disability benefits for sleep apnea, a veteran must generally show three things:
- A Current Medical Diagnosis
A VA-recognized sleep study (polysomnography) confirming obstructive, central, or complex sleep apnea.
- An In-Service Event, Injury, or Exposure
Evidence from service records, deployment history, or lay/buddy statements showing incidents or conditions during military service that could have caused or aggravated the sleep apnea (for example, hazardous exposure, facial injuries, or medications linked to weight gain).
- A Nexus Linking the Two
A medical opinion stating that it is “at least as likely as not” that the diagnosed sleep apnea is related to military service or to an already service-connected disability.
For direct service connection, VA generally considers evidence of a current disability, an in-service event, and a nexus between them. Evidence of secondary service connection may also be relevant.
Current VA Sleep Apnea Disability Ratings
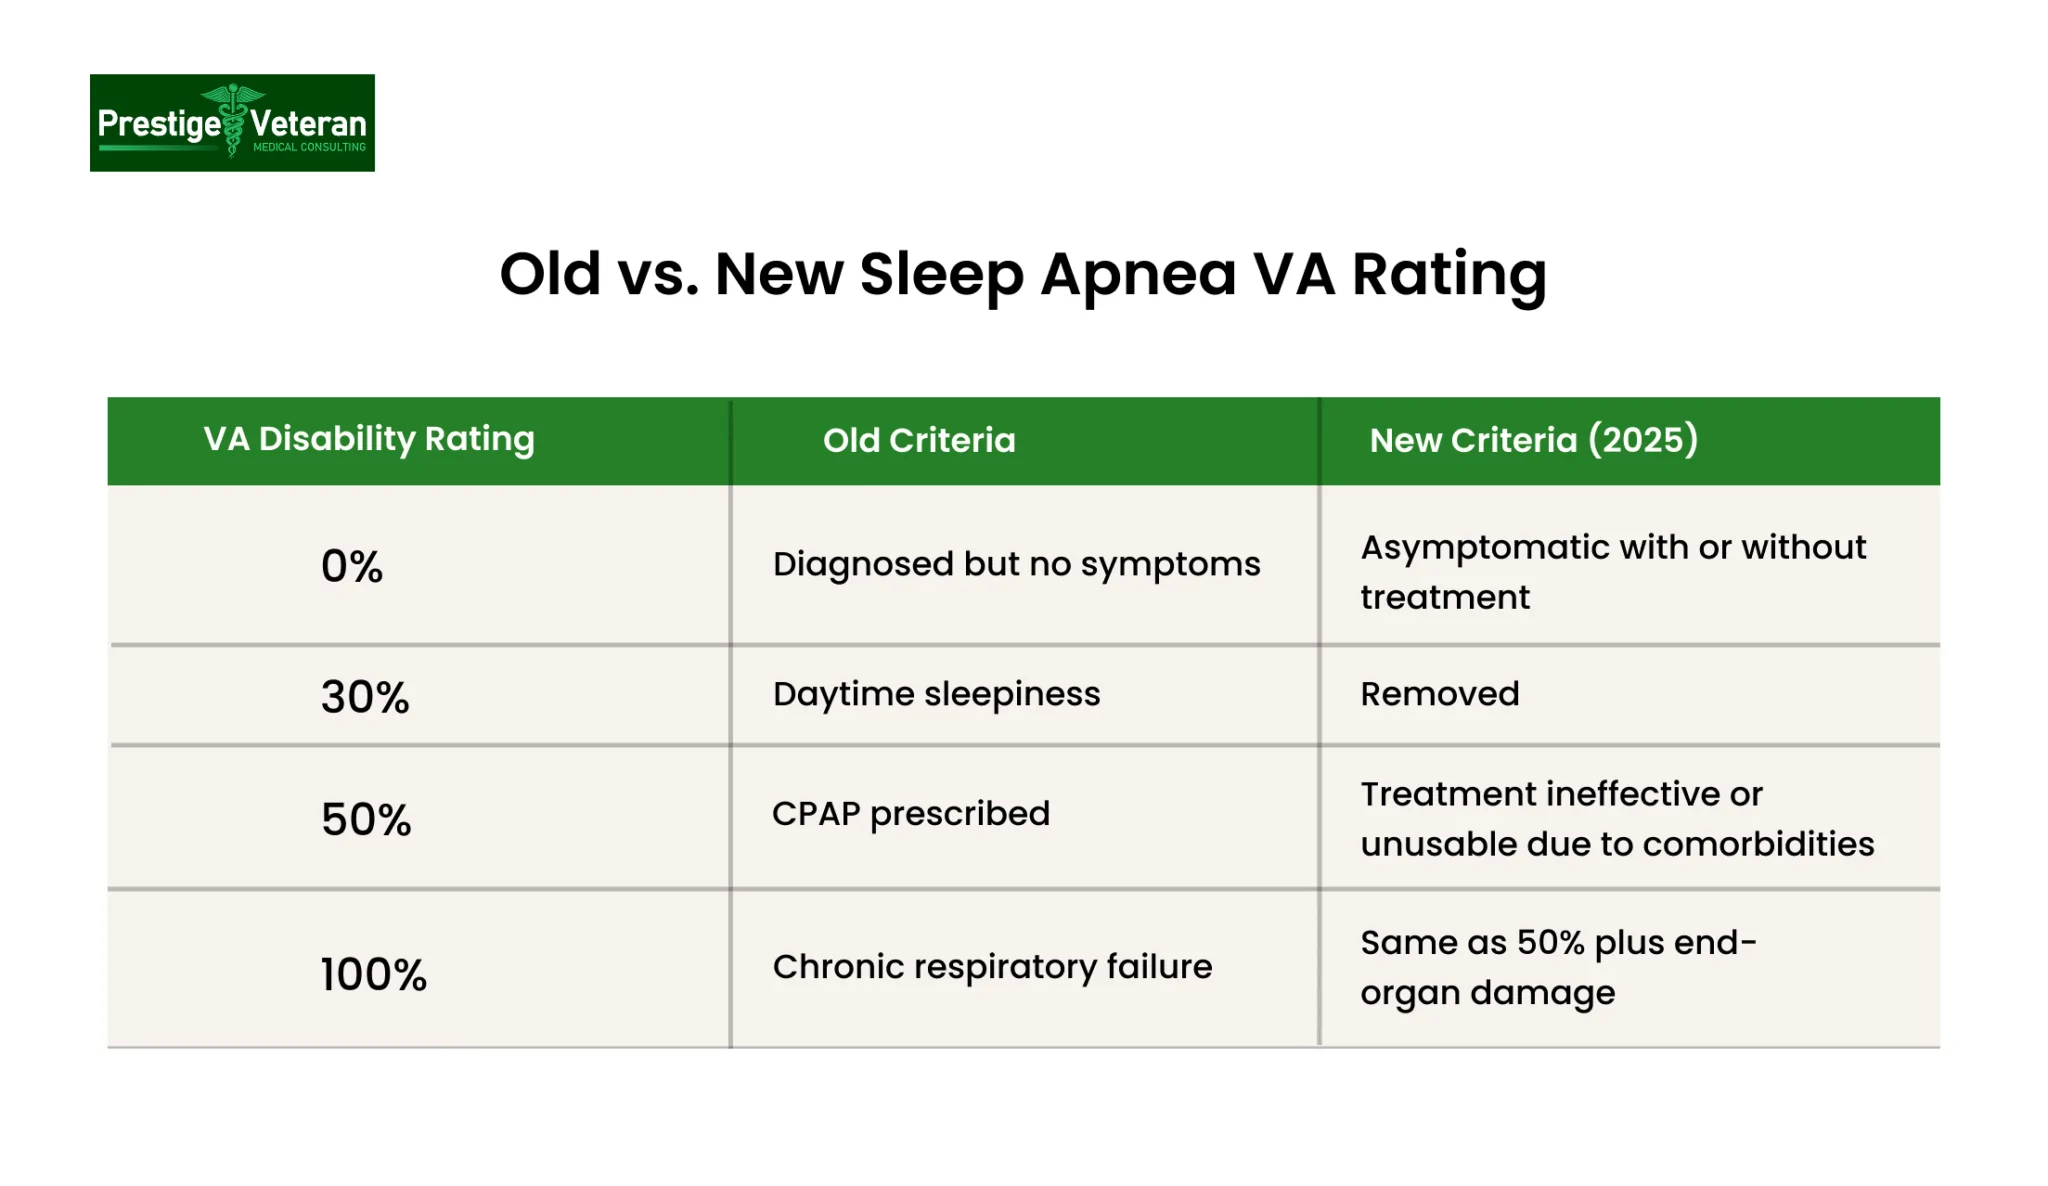
Under the current system, the VA rates sleep apnea under Diagnostic Code 6847 (38 C.F.R. § 4.97) at 0%, 30%, 50%, or 100% depending on the severity of symptoms and required treatment. The rating criteria are:
- 0% Rating: A veteran has a diagnosed condition but does not experience significant symptoms or require treatment. No monthly compensation for the rating itself.
- 30% Rating: The veteran has persistent daytime hypersomnolence (excessive sleepiness during the day). This rating qualifies for a monthly VA payment of about $552.47.
- 50% Rating: The veteran requires a CPAP (Continuous Positive Airway Pressure) machine or another breathing assistance device. A 50% rating warrants monthly compensation of roughly $1,132.90.
- 100% Rating: The veteran has chronic respiratory failure with carbon dioxide retention or cor pulmonale, or requires a tracheostomy. As a result, the veteran receives full monthly compensation of approximately $3,938.58. Rates with dependents appear in the 2026 VA disability pay chart.
*Rates assume a single veteran with no dependents; amounts may increase with dependents. View official disability pay rates here.
Under current DC 6847, a prescription for a CPAP machine is a criterion for a 50% rating.
Why Is the VA Changing Sleep Apnea Ratings?
The VA first proposed overhauling its respiratory ratings, including sleep apnea, in a Notice of Proposed Rulemaking published on February 15, 2022 (87 FR 8474). After reviewing public comments, the agency issued a Supplemental Notice of Proposed Rulemaking on September 12, 2024, with revised criteria (89 FR 74162). These changes remain proposed, not final, and are not in effect. Until a final rule is published in the Federal Register, sleep apnea continues to be rated under 38 C.F.R. § 4.97, Diagnostic Code 6847.
According to the VA, these proposed changes are part of an ongoing effort to modernize the Schedule for Rating Disabilities and align evaluations with current medical understanding (VA News, 2024).
Top Reasons Behind the Overhaul
The Department of Veterans Affairs has proposed changes to its sleep apnea rating system in response to concerns raised by lawmakers, medical professionals, watchdog groups, and veterans’ advocates:
- Automatic CPAP VA Rating: Under the current rating system, a prescription for a CPAP machine can support a 50% VA disability rating, regardless of whether the device is used regularly or if symptoms improve significantly.
- Treatment Over Impact: The existing approach has drawn criticism for basing disability ratings on treatment equipment rather than the functional impairment a veteran experiences.
- Medical Assessment: Under the current VA rating system, veterans with well-managed symptoms can receive the same rating as those with severe, treatment-resistant sleep apnea. The proposal would factor in treatment effectiveness, comorbidities, and end-organ damage when assessing functional impairment.
- Focus on Functional Impairment: The proposal would tie ratings to treatment effectiveness and the level of impairment, rather than a CPAP prescription alone.
Some veteran advocacy groups have argued that the proposed criteria may not account for the burden of ongoing CPAP use.
Under 38 U.S.C. § 1155, a schedule readjustment cannot by itself reduce a rating already in effect unless the disability has actually improved. The final rule’s terms, including its effective-date provisions, will control when it is published.
Major Proposed Changes to VA Sleep Apnea Ratings
The proposal would remove the 30% rating and revise the criteria for other evaluations. Under the proposal, a CPAP prescription alone would not determine a 50% rating; the VA would consider treatment effectiveness and impairment.
Proposed Sleep Apnea Ratings
- 0% Rating: The veteran is asymptomatic with or without treatment.
- 10% Rating: The veteran has sleep apnea but experiences incomplete relief from symptoms despite treatment, as determined by a sleep study.
- 50% Rating: The veteran has ineffective treatment (as found in a sleep study) or is unable to use prescribed treatment due to comorbid conditions, and without end-organ damage.
- 100% Rating: The veteran has ineffective or unusable treatment due to comorbid conditions and suffers from end-organ damage (significant damage to major organs like the heart, lungs, kidneys, or eyes caused by sleep apnea).
Under VAOPGCPREC 3-2000, the criteria in effect before a rule’s effective date apply to periods before that date; new criteria apply from the effective date forward, unless the rule provides otherwise. The final rule’s terms will control.
Current vs. Proposed VA Sleep Apnea Ratings
| VA Disability Rating | Current Rules (38 CFR §4.97 – DC 6847) | *Proposed Rules (if finalized as proposed) |
| 0% | Diagnosed, but no symptoms | Asymptomatic with or without treatment |
| 10% | Not available | Incomplete relief from symptoms despite treatment, as determined by a sleep study |
| 30% | Persistent daytime hypersomnolence | Removed |
| 50% | Requires CPAP or other breathing assistance | Treatment is ineffective or unusable due to comorbidities |
| 100% | Chronic respiratory failure with carbon dioxide retention or cor pulmonale, or tracheostomy | Treatment is ineffective or unusable due to comorbidities, plus end-organ damage |
VA’s Proposed Rule on Comorbid Conditions (Not Final as of Fall 2026)
In 2022, VA proposed revising DC 6847 to consider comorbid conditions when rating a veteran’s sleep apnea. These comorbidities can make standard sleep apnea treatments like CPAP machines ineffective or unusable and can also lead to end-organ damage. The proposed rule is not in effect as of fall 2026.
Under that proposed rule (not yet in effect), VA would take comorbid conditions into account, particularly when determining eligibility for a 50% or 100% rating.
What are the Comorbid Conditions for VA Sleep Apnea?
In the proposed rule, VA plans to add an informational note defining and giving examples of qualifying comorbid conditions as those that, according to a qualified medical provider, directly impede or prevent the use or implementation of a recognized treatment intervention that is normally considered effective.
The listed examples are contact dermatitis at the mask site, Parkinson’s disease, facial disfigurement, missing limbs, or skull fracture, conditions that directly interfere with sleep apnea treatment.
See 87 Fed. Reg. 8474 (Feb. 15, 2022).
Why Comorbidities Still Matter
Even under the current criteria (38 C.F.R. § 4.97, DC 6847), comorbid conditions can indirectly affect a VA claim for sleep apnea:
- They can appear in medical evidence showing the overall severity of a veteran’s health picture.
- They can be relevant to secondary service-connection claims, including when sleep apnea is caused or aggravated by another service-connected condition.
- They may help document why a veteran cannot tolerate or use a prescribed device, which could become relevant if VA finalizes its proposed rule.
Evidence Related to a Comorbid Condition and Rating
Evidence that may be relevant to evaluating a comorbid condition includes:
- Medical evidence of a secondary comorbid condition, such as a doctor’s diagnosis or treatment records.
- A nexus letter may provide a medical opinion linking the comorbid condition to sleep apnea or military service. It is not a required form of evidence.
- Sleep studies or other medical evidence addressing whether CPAP is effective or usable.
Under current DC 6847, a 100% rating requires chronic respiratory failure with carbon dioxide retention or cor pulmonale, or a tracheostomy. The proposed rule is not in effect; any revised criteria would depend on the final rule.
How Could These Proposed Changes Impact Veterans?
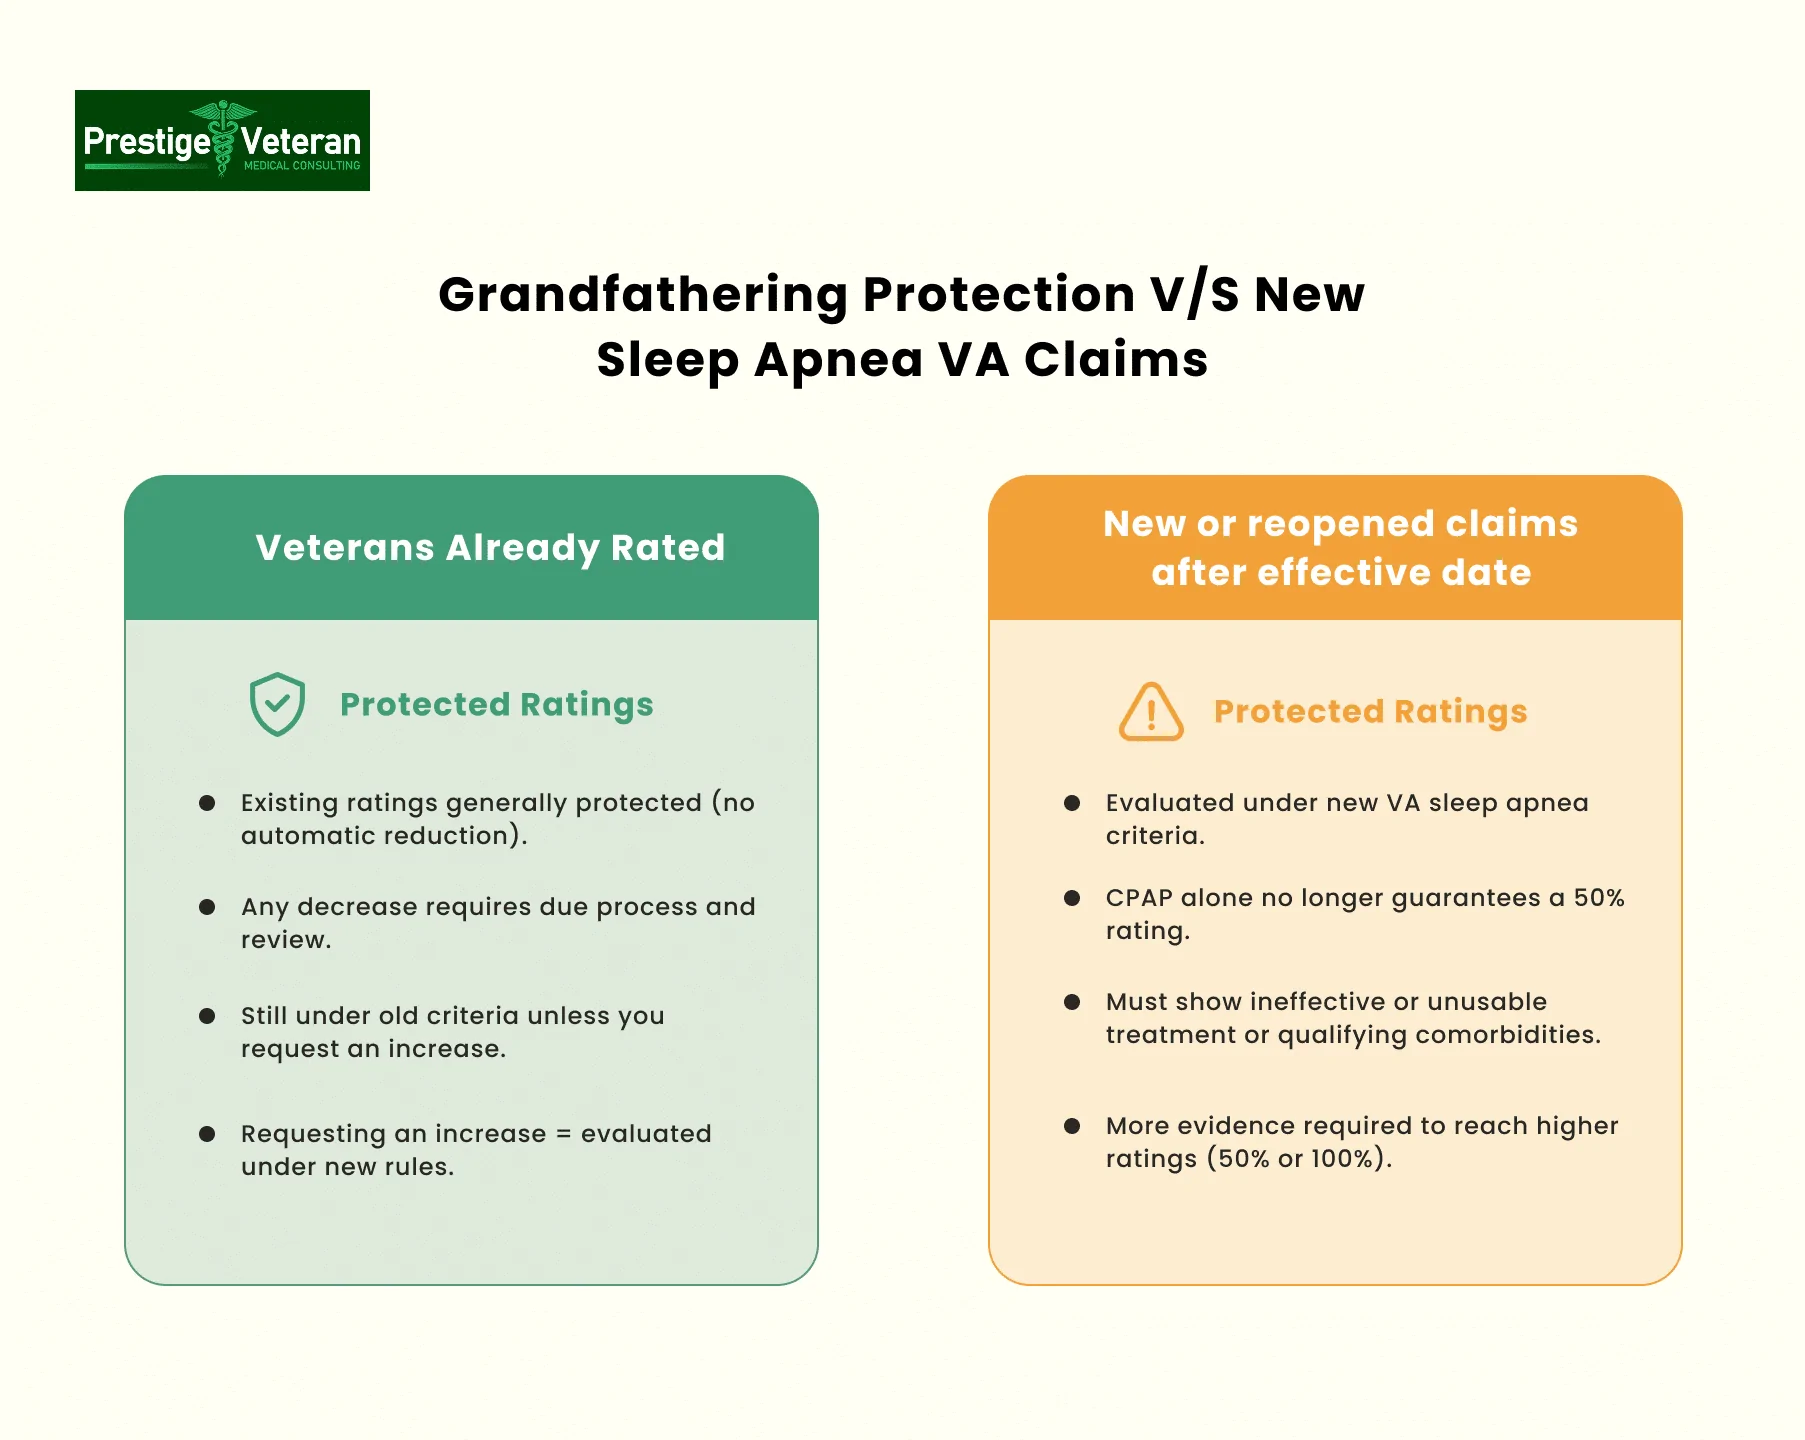
Veterans Already Receiving a Sleep Apnea Rating
A schedule readjustment by itself cannot reduce a rating already in effect unless the disability has actually improved (38 U.S.C. § 1155). Any final rule’s terms and applicable protections would govern. The proposed rule is not in effect as of fall 2026.
Veterans Filing New Claims
The proposed rule has not taken effect, and its effective-date provisions are not yet known. If a final rule is published, the final rule will establish the applicable effective date and terms.
Until a final rule takes effect, the current criteria apply. Under current DC 6847, a 50% rating requires use of a breathing assistance device such as a CPAP machine.
Veterans With Pending Claims
Under VAOPGCPREC 3-2000, the old criteria apply to periods before a change’s effective date. New criteria apply from the effective date forward, unless the final rule provides otherwise. The final rule’s terms will control. (VAOPGCPREC 3-2000, §3.114)
Veterans Requesting an Increased Rating
The proposed rule is not in effect as of fall 2026. A schedule readjustment by itself cannot reduce a rating already in effect unless the disability has actually improved under 38 U.S.C. § 1155; applicable due-process and protected-rating rules also apply. Prestige Veteran Medical Consulting publishes educational information about VA disability criteria. Prestige is not a law firm or VA-accredited claims agent, and this article is not legal advice.
How to Get VA Disability for Sleep Apnea?
Some advocates, including Ms. Deming, have commented publicly on the timing of claims relative to the proposed rule. The rule is not final, and its effective-date provisions are not yet known.
An Intent to File (ITF) can set a potential effective date if a complete claim is filed within one year (38 CFR § 3.155). Under VA’s generas
- If available, a completed DBQ for Sleep Apnea signed by a treating or VA provider
Step 6: VA Form 21-526EZ
VA Form 21-526EZ is the Application for Disability Compensation and Related Compensation Benefits used to file a disability compensation claim.
Relevant sections include:
- Section V: Conditions claimed may be listed here (e.g., “sleep apnea secondary to PTSD”). The form also requests information about military service history and treatment facilities.
- Section VI: This section includes military service dates, branches, and duty locations.
Last reviewed: Fall 2026. Educational information, not legal advice. Prestige Veteran Medical Consulting is not a law firm or VA-accredited claims agent.
Step 7: Claim Submission
Submission options include:
- Online at VA.gov
- By mail to the Evidence Intake Center
- In person through a Veterans Service Organization (VSO) or a VA-accredited attorney
Claim status is available at VA.gov/track-claims. Claim processing times vary.
Step 8: C&P Exam and Claim Status
VA may schedule a Compensation & Pension (C&P) exam. The exam may include questions about symptoms. Results from prior C&P exams may also be included with a VA disability application.
Under the current rating criteria, a 50% rating is assigned when use of a breathing assistance device such as a CPAP machine is required.
Legal Considerations
What If Your Claim Is in the Appeals Process?
Under VAOPGCPREC 3-2000, the criteria in effect apply to periods before a new rule’s effective date; new criteria apply from the effective date forward, unless the rule states otherwise. The proposed sleep apnea rule is not final, and its final effective-date provisions will control.
Proposed Rule Status and Existing Ratings
The sleep apnea rating revisions remain proposed and are not in effect as of fall 2026. The NPRM was published at 87 FR 8474 (Feb. 15, 2022), with a later VA document at 89 FR 74162. Under 38 U.S.C. § 1155, a schedule readjustment alone cannot reduce a rating already in effect unless the disability has actually improved. The final rule’s terms will control when it is published.
Sleep Apnea and Secondary Service Connection for VA Disability

VA may grant secondary service connection when medical evidence shows that another service-connected disability caused or aggravated sleep apnea. A separate secondary service connection award may affect a veteran’s combined rating and compensation.
The following are conditions sometimes considered in secondary claims under 38 C.F.R. § 3.310:
- Rhinitis & Sinusitis: Chronic nasal inflammation can narrow airways and may worsen or contribute to obstructive sleep apnea. Medical records showing long-term ENT treatment may be relevant to a nexus opinion.
- Post-Traumatic Stress Disorder (PTSD): Veterans with PTSD may experience hyperarousal, disrupted sleep cycles, and medication side effects that can contribute to weight gain and airway instability, potentially aggravating sleep apnea. PTSD and OSA also share a bidirectional relationship.
- Depression & Anxiety – These mental health conditions, or their prescribed medications, may contribute to weight gain and disrupted sleep, indirectly aggravating apnea. Stress-related claustrophobia can also interfere with effective CPAP use.
- Obesity (As an Intermediary Link: Weight gain related to service-connected conditions, such as PTSD or medications, may be considered as an intermediate step between the service-connected condition and sleep apnea. VA treats obesity as a possible intermediate step, not as a disability on its own (VAOPGCPREC 1-2017).
- Gastroesophageal Reflux Disease (GERD): Nighttime reflux due to GERD can irritate the throat and may interfere with comfortable breathing during sleep, making it harder for veterans to tolerate CPAP therapy.
- Asthma: Asthma may lead to ongoing airway inflammation and obstruction, heightening the risk of sleep-disordered breathing.
Evidence: Evidence considered in a secondary claim may include a medical nexus opinion linking a primary service-connected condition to sleep apnea, sleep study results, and records of ongoing treatment.
Some related conditions, including chronic rhinitis, sinusitis, and asthma, may qualify for presumptive service connection for veterans with qualifying service and exposure (effective August 5, 2021; see 86 Fed. Reg. 42,724). This presumption applies to the listed respiratory conditions; it does not by itself establish presumptive service connection for sleep apnea.
VA evaluates secondary service connection claims based on the evidence and applicable criteria.
Qualifying for TDIU with Sleep Apnea
Total Disability based on Individual Unemployability (TDIU) may provide compensation at the 100% rate to veterans whose service-connected disabilities prevent substantially gainful employment, even if their combined VA rating is below 100%.
Veterans with OSA may experience severe daytime fatigue, memory issues, cardiovascular issues, and impaired concentration, which can limit their ability to maintain gainful employment.
To qualify for TDIU under 38 C.F.R. § 4.16(a) (schedular), veterans generally need:
- A single disability rated at 60% or
- A combined rating of 70% with at least one condition rated 40%.
Veterans who do not meet the percentage thresholds but cannot work may be considered for extraschedular TDIU under § 4.16(b).
Evidence VA may consider includes medical opinions, employer statements, and lay testimony describing how sleep apnea interferes with work. VA Form 21-8940 is used to apply for TDIU; the form is available here: VA Form 21-8940.
VA C&P Exams for Sleep Apnea
A VA Compensation & Pension (C&P) exam for sleep apnea is one part of the VA’s evaluation of a veteran’s disability claim. Conducted by a VA or contracted medical professional, this exam may address the diagnosis, its relationship to military service, and the condition’s impact on life and functionality.
What to Expect:
- During the exam, the C&P examiner may review the veteran’s medical history, including prior sleep studies, treatments, and any use of breathing assistance devices like a CPAP machine.
- The examiner may also evaluate secondary conditions like PTSD, obesity, or heart disease that may be associated with or aggravate sleep apnea.
- Questions may address the onset and progression of symptoms such as loud snoring, gasping or choking during sleep, daytime hypersomnolence, or use of a CPAP or BiPAP machine.
- The examiner may ask how sleep apnea affects work, daily tasks, and social interactions.
- The examiner will complete a Sleep Apnea Disability Benefits Questionnaire (DBQ), which guides VA raters in evaluating claims.
Relevant Evidence:
Relevant evidence may include sleep study results, CPAP compliance and usage records, and statements describing functional limitations.
Examples of reported functional effects include “I’m constantly exhausted during the day and have trouble focusing at work due to poor sleep.”
The VA may conduct an ACE (records-only) review without an in-person evaluation. In either format, the examiner records information about the condition, and VA considers the exam findings and other evidence when evaluating the claim.
The Essential Role of Nexus Letters in Sleep Apnea VA Claims
In VA sleep apnea claims, nexus letters may provide medical evidence about the relationship between sleep apnea and military service or a service-connected condition.
A nexus letter is an independent medical opinion written by a licensed physician or healthcare provider explaining whether sleep apnea is at least as likely as not caused or worsened by military service or a service-connected condition.
A nexus letter may address:
- Clear medical rationale using “at least as likely as not” language
- Explanation of why comorbid conditions make the treatment intolerable
- Documentation of End-Organ Damage, if applicable
- Reference to medical records, including sleep studies, treatment history, and documentation of symptoms
Nexus letters are not legally required. VA may consider them as medical evidence when evaluating service connection or an appeal.
Case Study: 50% VA Sleep Apnea Rating
A 38-year-old former Army veteran served on active duty from 2005 to 2013 with multiple deployments. During service, his medical records documented chronic fatigue, difficulty staying awake during duty hours, and repeated complaints from roommates about loud snoring and pauses in breathing at night.
Following separation, his symptoms worsened, leading to morning headaches, impaired concentration, and elevated blood pressure. In 2024, a polysomnography confirmed a diagnosis of obstructive sleep apnea (OSA), and he was prescribed a continuous positive airway pressure (CPAP) machine.
Under the current criteria, use of a CPAP machine is a criterion for a 50% VA disability rating, subject to VA’s evaluation of the claim.
Evidence in the Example:
- Service treatment records and witness statements showing in-service symptoms
- Post-service medical records documenting worsening of symptoms
- A 2024 polysomnography confirming OSA diagnosis and CPAP prescription
- A medical nexus opinion from a board-certified pulmonologist linking the veteran’s current OSA to documented in-service symptoms
- Evidence of secondary conditions (e.g., elevated blood pressure) relevant to the impact and history of OSA
Nexus Statement:
“It is my professional medical opinion that it is at least as likely as not (a 50% probability or greater) that the veteran’s currently diagnosed obstructive sleep apnea (OSA) began during or is directly related to his active military service.”
(This example is for educational purposes only and does not constitute legal or medical advice.)
Authored by:
Rebecca Deming, Esq.
VA-Accredited Attorney, ProVet Legal
Specializing in VA disability law and military medical appeals
Medically Reviewed by:
Board-Certified Pulmonologist
VA Sleep Apnea Rating Changes: Proposed, Not Final
Some advocates have commented publicly on the timing of claims relative to the proposed rule. Under VA’s general practice, the rating criteria in effect for a given period apply to that period.
FAQs
What is the effective date for the VA sleep apnea rating changes?
The Department of Veterans Affairs has proposed updates to its sleep apnea rating criteria. The proposal is not final or in effect, and the effective-date provisions of any final rule are not yet known.
What criteria apply to higher sleep apnea ratings?
Under current DC 6847, a 100% rating requires chronic respiratory failure with carbon dioxide retention or cor pulmonale, or a tracheostomy. The proposed criteria for a 50% rating are summarized above.
Will the VA automatically decrease my current rating?
A schedule readjustment alone cannot reduce a rating already in effect unless the disability has actually improved (38 U.S.C. § 1155).
If I submit my claim now, but the VA doesn’t decide until after the sleep apnea changes effective date, which rules will be used?
Under VAOPGCPREC 3-2000, the criteria in effect for each period generally apply, subject to the final rule’s terms.
Will using a CPAP machine still qualify for a 50% rating?
Under current rules, a CPAP prescription is a criterion for a 50% rating. Under the proposal, a 50% rating would require evidence of ineffective treatment or treatment that is unusable due to comorbidities.
What’s considered “ineffective treatment”?
The proposal describes ineffective treatment as treatment found ineffective by a sleep study.
What will justify a 100% rating for a sleep apnea VA claim?
Under current DC 6847, a 100% rating requires chronic respiratory failure with carbon dioxide retention or cor pulmonale, or a tracheostomy. The proposed rule is not final, and its final terms will control.
Will VA check CPAP compliance data?
VA may review CPAP prescription and usage records when evaluating a claim.
What counts as “end-organ damage”?
In the proposed criteria, end-organ damage means significant, medically documented harm to major organs such as the heart, lungs, kidneys, or eyes caused or aggravated by sleep apnea.
Do I need a new sleep study?
VA requires a sleep study to confirm a sleep apnea diagnosis (38 CFR § 4.97, Note to DC 6847). Medical evidence may also address the condition’s severity and whether treatment is effective or unusable.
How does secondary to PTSD/GERD work?
VA can grant secondary service connection under 38 CFR § 3.310 when a service-connected condition causes or aggravates another condition. VA treats obesity as a possible intermediate step, not as a disability on its own (VAOPGCPREC 1-2017).
Also read: The Role of a Nexus Letter for Obstructive Sleep Apnea (OSA) Claims
Prestige Veteran Medical Consulting is not a law firm, accredited claims agent, or affiliated with the Veterans Administration or Veterans Services Organizations. Only VA-accredited attorneys, claims agents, and VSO representatives can assist with claims; VA’s accreditation search lists them.