Last reviewed November 8, 2026.
Degenerative disc disease (DDD) is one of the most common spine conditions veterans claim with the VA. Years of rucking, heavy lifting, hard landings, and repetitive physical strain can wear on the discs that cushion the spine. Symptoms may not show up until years after service.
This guide explains what DDD is, how it can be connected to service, how the VA rates it, and what evidence tends to matter.
Table of Contents
What Is Degenerative Disc Disease?
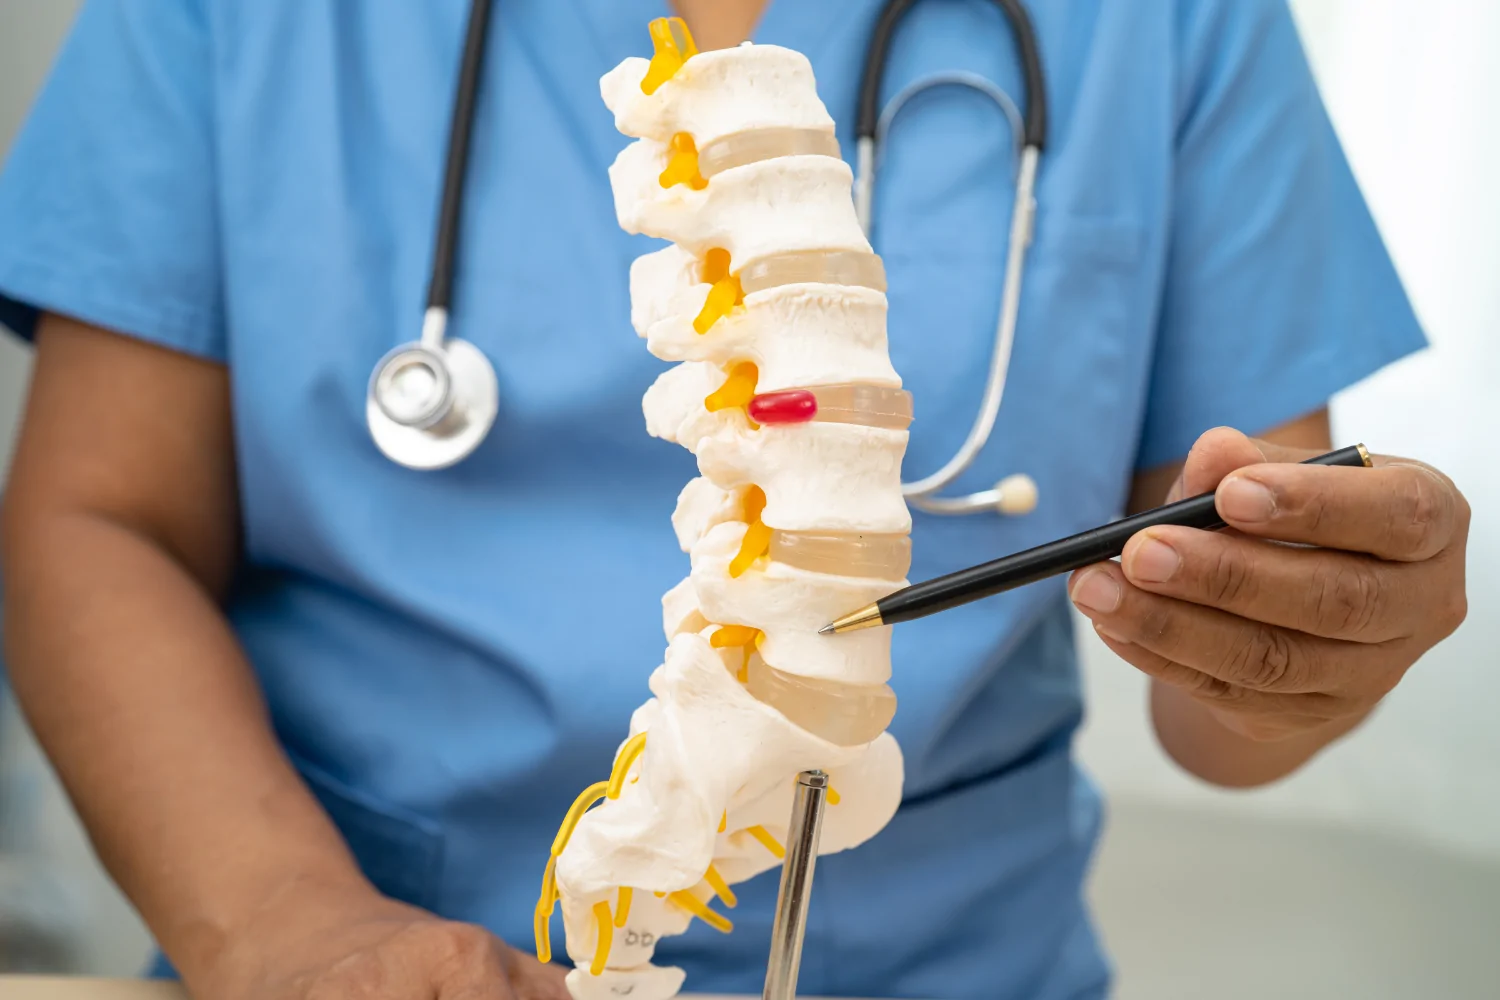
Despite the name, degenerative disc disease is not technically a disease. It describes the gradual breakdown of the intervertebral discs, the shock absorbers between the vertebrae. When discs lose height, hydration, or cushioning, veterans may experience:
- Chronic low back or neck pain
- Pain that worsens with sitting, bending, lifting, or twisting
- Bulging or herniated discs
- Pain, numbness, or tingling radiating into the arms or legs (radiculopathy)
- Muscle spasms, stiffness, and reduced mobility
Between 2001 and 2010, 131,986 active-duty U.S. service members were diagnosed with DDD. That is a crude incidence rate of about 951 per 100,000 person-years, and the yearly rate more than doubled over that period.
Why Veterans Are at Higher Risk
Military duties often load the spine in ways most civilian jobs do not:
- Infantry soldiers may carry 60 to 100 pounds of gear, often for hours at a time. (See what years of body armor do to veterans’ spines.)
- Paratroopers absorb repeated hard landings.
- Mechanics, aircrew, and engineers often work in awkward, sustained positions.
- Years of physical training add repetitive stress.
A veteran does not need to have been diagnosed with DDD on active duty for service to matter. The question is whether the evidence supports a link between service and the current condition. For more on this, see why veterans can develop degeneration earlier than expected.
Medical Literature and Supporting Evidence
Medical literature can help explain why a particular veteran’s DDD is more than ordinary aging. It is most useful when it is applied to that veteran’s history.
- Disc degeneration has more than one cause. Adams and Roughley (Spine, 2006) describe disc degeneration as structural failure combined with accelerated or advanced signs of aging. They identify genetic inheritance, aging, inadequate nutrient transport, and loading history as contributing factors. Loading history is where military duties may be relevant.
- Imaging alone does not prove a cause. A large systematic review in the American Journal of Neuroradiology (Brinjikji et al., 2015) found that disc degeneration, bulges, and protrusions are common on imaging in people with no symptoms, and become more common with age. An MRI confirms the diagnosis, but the medical reasoning has to explain why service contributed.
- Altered mechanics can matter. When a service-connected knee, hip, ankle, or foot condition changes how a veteran walks or stands, a clinician may consider whether that added strain contributed to spine degeneration. That depends on the individual record.
When literature is cited in a nexus letter, it should support reasoning about the veteran’s own history, not replace it.
How the VA Rates Degenerative Disc Disease
DC 5242 versus DC 5243
Under 38 CFR 4.71a, degenerative disc disease is generally rated under Diagnostic Code 5242 (“degenerative arthritis, degenerative disc disease other than intervertebral disc syndrome”).
Diagnostic Code 5243 (intervertebral disc syndrome, or IVDS) is assigned only when there is disc herniation with compression or irritation of the adjacent nerve root. All other disc diagnoses go under DC 5242.
General Rating Formula for the Spine
DC 5242 uses the General Rating Formula for Diseases and Injuries of the Spine. It applies “with or without symptoms such as pain (whether or not it radiates), stiffness, or aching.”
Thoracolumbar spine (mid and low back):
| Rating | Criteria |
|---|---|
| 10% | Forward flexion greater than 60° but not greater than 85°; or combined range of motion greater than 120° but not greater than 235°; or muscle spasm, guarding, or localized tenderness not causing abnormal gait or spinal contour; or vertebral body fracture with loss of 50% or more of height |
| 20% | Forward flexion greater than 30° but not greater than 60°; or combined range of motion not greater than 120°; or muscle spasm or guarding severe enough to cause abnormal gait or abnormal spinal contour (such as scoliosis, reversed lordosis, or abnormal kyphosis) |
| 40% | Forward flexion 30° or less; or favorable ankylosis of the entire thoracolumbar spine |
| 50% | Unfavorable ankylosis of the entire thoracolumbar spine |
| 100% | Unfavorable ankylosis of the entire spine |
Cervical spine (neck):
| Rating | Criteria |
|---|---|
| 10% | Forward flexion greater than 30° but not greater than 40°; or combined range of motion greater than 170° but not greater than 335°; or spasm, guarding, or localized tenderness not causing abnormal gait or contour |
| 20% | Forward flexion greater than 15° but not greater than 30°; or combined range of motion not greater than 170°; or spasm or guarding severe enough to cause abnormal gait or contour |
| 30% | Forward flexion 15° or less; or favorable ankylosis of the entire cervical spine |
| 40% | Unfavorable ankylosis of the entire cervical spine |
| 100% | Unfavorable ankylosis of the entire spine |
The neck and the mid/low back are rated separately unless both are fixed in unfavorable ankylosis.
When IVDS applies
If a veteran has a herniated disc compressing or irritating a nerve root (DC 5243), the VA rates it under whichever formula gives the higher result. That is either the General Rating Formula above or the incapacitating-episodes formula:
| Rating | Incapacitating episodes in the past 12 months |
|---|---|
| 10% | At least 1 week but less than 2 weeks total |
| 20% | At least 2 weeks but less than 4 weeks total |
| 40% | At least 4 weeks but less than 6 weeks total |
| 60% | At least 6 weeks total |
An incapacitating episode is a period of acute symptoms that requires bed rest prescribed by a physician and treatment by a physician. Missed work or self-directed rest does not count unless it is documented that way.
Nerve involvement is rated separately
The rating formula directs the VA to rate associated objective neurologic problems separately. That includes radiculopathy, bowel impairment, and bladder impairment. Sciatic radiculopathy, for example, is usually rated under the peripheral nerve codes. See our guides to sciatica VA ratings and radiculopathy.
Painful motion
Under 38 CFR 4.59, the rating schedule intends to recognize actually painful joints as entitled to at least the minimum compensable rating for the joint. Painful motion should be documented at the exam.
Proving Service Connection
Service connection generally needs three pieces:
- A current diagnosis of DDD, usually confirmed by imaging and clinical findings
- An in-service event, injury, or duty, such as heavy lifting, a fall, a vehicle accident, or airborne operations
- A medical nexus explaining how the current condition is related to service
Direct service connection
Example: an infantry soldier who regularly carried 80-pound rucksacks for a decade went to sick call for back pain several times. Years later, an MRI confirmed disc degeneration. Service treatment records, consistent post-service treatment, and a reasoned medical opinion can support a direct claim.
Secondary service connection
DDD can also develop from, or be worsened by, another service-connected condition:
- Knee, hip, ankle, or foot conditions, including flat feet, which can change gait and posture
- Obesity as an intermediate step, when weight gain results from another service-connected condition or its treatment
- Traumatic brain injury, when balance problems and abnormal movement patterns are documented
Example: a veteran service-connected for knee instability develops chronic low back pain after years of altered walking mechanics. Imaging confirms DDD, and the claim is filed as secondary to the knee.
For a sample of how secondary reasoning can be written, see our sample nexus letter for low back pain.
Conditions Secondary to Degenerative Disc Disease
DDD itself can lead to other conditions that may be claimed separately when they are diagnosed and medically linked:
- Radiculopathy: nerve root compression causing radiating pain, numbness, or weakness
- Spinal stenosis: narrowing of the spinal canal
- Spondylolisthesis: one vertebra slipping forward over another
- Cervicogenic or tension headaches from cervical disc disease
- Depression or anxiety related to chronic pain and loss of function
The VA avoids rating the same symptoms twice (pyramiding), so each secondary condition needs its own diagnosis and its own symptoms. See our full list of conditions related to back pain.
Preparing for a C&P Exam for DDD
The examiner will measure range of motion with a goniometer and note pain, spasm, guarding, and gait. They will also ask about flare-ups and test for nerve involvement.
- Describe your flare-ups: how often they happen, how long they last, and what you cannot do during them.
- Stop a movement when pain begins. Don’t push through it.
- Bring imaging, treatment records, and a symptom log.
- Mention radiating symptoms, numbness, or bladder or bowel changes.
More detail: low back pain C&P exam and how the VA measures range of motion.
Common Challenges
- “It’s just age.” The VA may attribute degeneration to aging. A well-reasoned opinion addresses age directly instead of ignoring it.
- Missing records. Gaps in treatment make the timeline harder to follow.
- Flare-ups not captured. If flare-ups aren’t described at the exam, the rating may not reflect them.
- IVDS episodes not documented. Without physician-prescribed bed rest in the records, the incapacitating-episode formula usually can’t be used.
If a claim is denied or underrated, the options include a Higher-Level Review, a Supplemental Claim with new evidence, or a Board appeal. An accredited representative can advise on which path fits your case.
TDIU and Degenerative Disc Disease
When service-connected disabilities prevent substantially gainful employment, a veteran may qualify for Total Disability based on Individual Unemployability. Under 38 CFR 4.16(a), the schedular requirement is either:
- one service-connected disability rated at 60% or more, or
- two or more disabilities with at least one rated at 40% or more, and a combined rating of 70% or more.
Final Thoughts
DDD claims usually turn on three things:
- a clear diagnosis;
- a documented history connecting the condition to service, or to another service-connected condition;
- an exam that captures how the condition actually limits the veteran, including flare-ups and nerve symptoms.
FAQs
What is the highest VA rating for degenerative disc disease?
Under the General Rating Formula, 100% requires unfavorable ankylosis of the entire spine. For IVDS rated on incapacitating episodes, the maximum is 60%. Separate ratings for radiculopathy, and TDIU, can raise the overall compensation.
Is degenerative disc disease rated as IVDS?
Usually not. Since the current rule, DC 5243 (IVDS) is assigned only when a disc herniation compresses or irritates a nerve root. Other disc diagnoses are rated under DC 5242.
What is the difference between IVDS and degenerative disc disease?
DDD describes gradual wear and breakdown of the discs. For VA purposes, IVDS refers to disc herniation that compresses or irritates a nerve root.
Can you fully recover from degenerative disc disease?
DDD is a chronic condition. Symptoms can often be managed with treatment, but the structural changes generally do not reverse.
Can I run with degenerative disc disease?
It depends on your symptoms and findings. High-impact activity can aggravate symptoms for some people, so ask your treating clinician what is appropriate for you.
What conditions are secondary to degenerative disc disease?
Radiculopathy, spinal stenosis, spondylolisthesis, headaches, depression, and anxiety are among the conditions that can develop secondary to DDD.
Also read: Qualifying for a Lumbosacral Strain VA Disability Rating
At Prestige Veteran Medical Consulting, a veteran-owned company, we specialize in Independent Medical Opinions (IMOs) known as Nexus letters.
Our purpose is to empower YOU, the veteran, to take charge of your medical evidence and provide you with valuable educational tools and research to guide you on your journey.
Understanding the unique challenges veterans face, our commitment lies in delivering exceptional service and support.
Leveraging an extensive network of licensed independent medical professionals, all well-versed in the medical professional aspects of the VA claims process, we review the necessary medical evidence to incorporate in our reports related to your VA Disability Claim.
Prestige Veteran Medical Consulting is not a law firm, accredited claims agent, or affiliated with the Veterans Administration or Veterans Services Organizations. However, we are happy to discuss your case with your accredited VA legal professional.